
Taking one HIV tablet a day is wonderfully effective – but “every day” still adds up to many thousands of tablets over a lifetime
Islatravir and lenacapavir could reduce that burden to one tablet a week; the investigational combination has shown success in two Phase 3 trials of HIV-sustained suppressors
marking a major step toward the first ever complete once-weekly oral HIV treatment regimen, if and when it becomes approved.
How do the two drugs work?
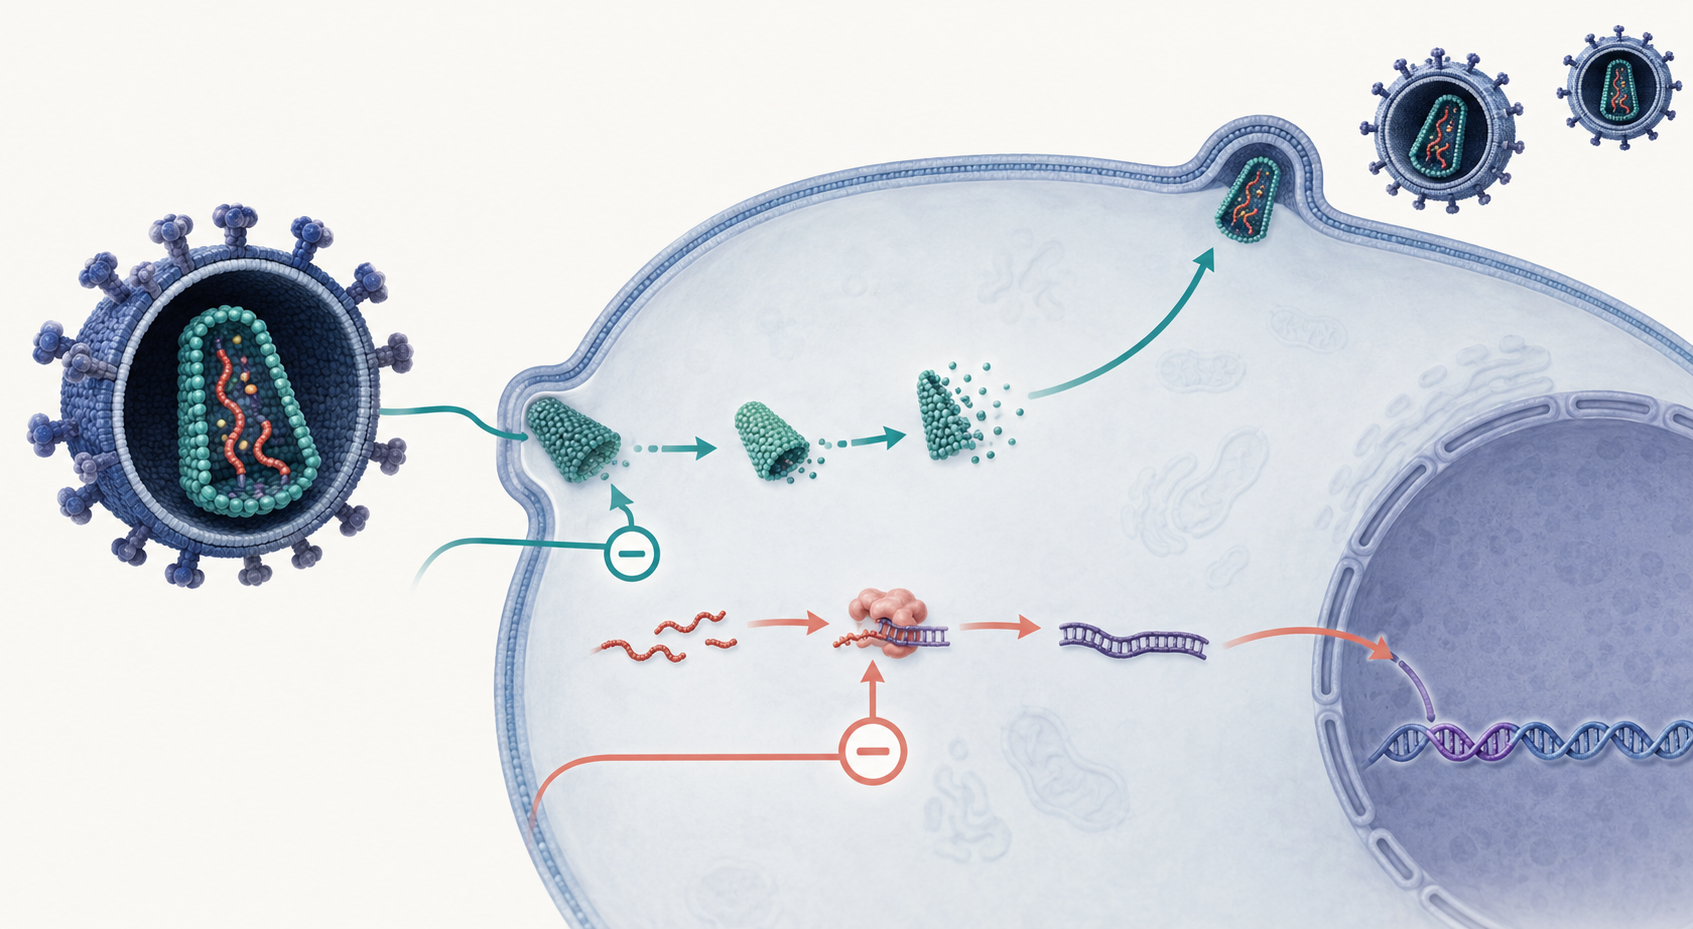
HIV uses a number of biochemical processes to replicate, and so successfully treating it often involves a combination of drugs that target different steps in the process
Islatravir is a “nucleoside reverse transcriptase translocation inhibitor” (don’t worry, we’ll get to what that means in a sec), while lenacavir is a “capsid inhibitor”. In short, they work by targeting different enzymes used by HIV, and both have long enough half-lives to be taken once a week. The two together provide a synergistic effect, making it harder for the HIV to develop resistance.
A guide to antiviral medication explains why targeting multiple steps in a virus’s replication cycle often leads to increased effectiveness
What were the results of the trials?
ISLEND-1 and ISLEND-2 were trials of an investigational combination of islatravir and lenacapavir in treatment-experienced adults with HIV who were virally suppressed (had an undetectable viral load). Patients were switched from a daily oral HIV regimen to a once-weekly combination of 2 mg islatravir and 300 mg lenacapavir.
In the first trial, ISLEND-1, this once-weekly combination was compared to a daily Biktarvy regimen.
At 48 weeks, none of the patients taking the once-weekly combination had a viral load over 50 copies per mL, versus 1 patient (0.3%) in the Biktarvy group.
In ISLEND-2, the once-weekly combination was compared to other daily regimens; treatment with once-weekly islatravir/lenacapavir had a 0.3% rate of virologic nonsuppression compared to 1.3% for the daily regimens.
Thus, the once-weekly combination was non-inferior to the daily treatments in both trials, with regard to maintaining a suppressed viral load.
The patients who switched to the once-weekly combination also had higher rates of treatment satisfaction and lower treatment burden
What were the side effects?
Overall, the trial regimens were similar to the comparator treatments in terms of safety, and CD4+ T cell and lymphocyte levels remained stable throughout the 48 weeks.
In ISLEND-1, 13.5% of the once-weekly treatment group reported treatment-related adverse events, compared to 13.2% in the Biktarvy group. The most common side effects were nausea and headaches. ISLEND-2 had higher rates of treatment-related adverse events for the once-weekly group as well; headaches, nausea, and diarrhea were the most common. Discontinuation due to side effects was rare in both cases. Earlier in the development of islatravir, higher doses had been linked to decreases in lymphocyte and CD4+ T cell levels (among other issues) and so the lower dose once-weekly combination is reassuring in that regard, but longer-term trials are needed.
Who would benefit from a weekly HIV pill?
The trials mentioned were switch trials; all the patients involved were doing well on their previous daily HIV treatment regimens.
Thus, these trials cannot say much about whether such a once-weekly combination would be beneficial earlier in the course of infection, or in people with an unsuppressed viral load or who have developed resistance to HIV treatments
A once-weekly oral HIV regimen would be a welcome change for many people, however; if they are bothered by the daily reminder of their HIV status, or have trouble adhering to a daily regimen when they travel or have other disruptions to their routines, or are concerned about privacy and discreet dosing, then a weekly pill could potentially improve their quality of life.
It would also be a valuable alternative to long-acting injectables for people who want to avoid regular doctor’s visits and injections but still want an infrequent HIV treatment; weekly dosing would be much easier than the standard 6-monthly injections. However, a once-weekly regimen is still a daily regimen, just with more time between doses. Patients would have to be especially careful not to miss a dose, as doing so would leave them with a much larger “window” between doses for the virus to rebound. Missed-dose guidelines and resistance data could be crucial in determining how such a drug would be used if it became available. Most importantly, patients must not attempt to switch, discontinue, or modify their HIV treatment in any way without the explicit approval of an HIV care provider.
Is it FDA approved?
Not yet; islatravir and lenacapavir as a once-weekly combination are still investigational, but Gilead and Merck (the companies which make the drugs) intend to use the results of these Phase 3 trials to submit to the relevant regulatory agencies. Approval will depend on the full results of the trials, including longer-term follow-up, information on resistance, manufacturing details, etc. For now, daily antiretroviral therapy remains the standard of care for oral HIV treatment, as it effectively suppresses the virus and preserves immune function. With good adherence, a daily regimen can also prevent sexual transmission of HIV; when the viral load is undetectable, it cannot be transmitted through sex.
The once-weekly combination will not be a cure for HIV, but if approved it could help some patients to manage their treatment with less disruption to their everyday lives.
